Hair Transplant Risks: Understanding and Minimizing Complications
Part of our comprehensive hair transplant guide, this section covers the potential risks and complications you should know about. Hair transplants are generally safe. But "safe" doesn't mean risk-free. Understanding potential complications, from minor and temporary (swelling, itching) to rare but serious (infection, necrosis), helps you make an informed decision and recognize warning signs early.
A 2026 review of follicular unit extraction (FUE) complications says one estimate put the overall complication rate at "approximately 1%-5%, although these data were derived from historical series using mainly the FUT technique." FUT means follicular unit transplantation. A retrospective study of 1,030 FUE procedures "reported notable complications in 9.9% of cases; however, nearly half of the patients experienced mild postoperative events, most commonly slight frontal edema and donor-site pruritus": mild forehead swelling and itching where hair grafts, small groups of transplanted hairs, were taken (Frontiers in Medicine review, read 27 September 2026).
This guide covers every risk category, how to prevent problems, and what to do if complications occur.
Risk Categories
Common and Temporary
- Swelling
- Itching
- Scabbing
- Temporary shock loss
- Minor bleeding
Less Common but Manageable
- Infection
- Folliculitis (inflamed follicles)
- Cyst formation
- Poor graft survival in specific areas
- Numbness (prolonged)
Rare but Serious
- Skin necrosis (tissue death)
- Severe infection
- Permanent shock loss
- Keloid/hypertrophic scarring
- Nerve damage

Common Temporary Risks
Swelling
What happens:
- Fluid accumulation in forehead, sometimes around eyes
- Swelling peaks "around 2-3 days after surgery" and resolves "within 5-7 days." "In FUE cohorts, frontal edema has been observed in nearly half of patients, making it the most common early postoperative finding, while periorbital swelling occurs in approximately 3%-5%" (Frontiers in Medicine review, read 27 September 2026)
Why it happens:
- Normal inflammatory response to surgery
- Gravity pulls fluid down from scalp
Prevention:
- Sleep elevated: among preventive measures the review lists "intermittent cold compresses and head elevation (20-30 °) during the first postoperative days" (Frontiers in Medicine review, read 27 September 2026)
- Ice packs on forehead (NOT on grafts)
- Ask your surgeon which medication, if any, to take for swelling. The review lists corticosteroids given around the time of surgery (Frontiers in Medicine review, read 8 November 2026).
Warning signs:
- Swelling that keeps getting worse (may indicate infection)
- Severe eye swelling preventing vision
Itching
What happens:
- Itching in transplanted and donor areas
- Itching is "usually mild, appearing within the first postoperative week and resolving spontaneously within several days or weeks." "In a small proportion of patients, itching may persist for several months after surgery" (Frontiers in Medicine review, read 27 September 2026)
Why it happens:
- Healing process
- New hair follicles activating
Prevention/Management:
- Ask your surgeon about antihistamines if itching is moderate or persists (Frontiers in Medicine review, read 8 November 2026).
- Resist scratching (can dislodge grafts)
- Gentle tapping instead of scratching
- Saline spray or a moisturizing emollient (ask your clinic what it gives you; Frontiers in Medicine review, read 8 November 2026).
Not normal:
- Itching with increasing redness/pus (suggests infection)
Scabbing
What happens:
- Small scabs form around each graft
- "Crust formation is a normal part of postoperative healing after FUE, typically appearing within 2-3 days and resolving spontaneously by 7-10 days with appropriate care" (Frontiers in Medicine review, read 27 September 2026)
Prevention:
- Gentle washing starting day 2-3
- Don't pick at scabs
- Let them fall off naturally
Complications:
- Picking scabs can dislodge grafts
- Scabs that last longer: "Persistent crusts beyond 2 weeks should therefore be evaluated, as they may indicate delayed healing" (Frontiers in Medicine review, read 27 September 2026)
Minor Bleeding
What happens:
- The review describes "mild postoperative oozing first 24-48 h" and says "postoperative bleeding is uncommon and typically self-limited" (Frontiers in Medicine review, read 27 September 2026)
- Light spotting on pillow normal
Prevention:
- Avoid blood thinners before surgery
- Sleep elevated
- Don't touch grafts
Warning signs:
- Bleeding that continues beyond the first 24-48 hours
- Bleeding that won't stop with gentle pressure
Temporary Shock Loss
What happens:
- Existing (non-transplanted) hair near transplant area sheds
- Caused by surgical trauma
- It "typically occurs within 2-8 weeks after surgery, with regrowth usually beginning around 3 months postoperatively. Reported incidence varies widely, ranging from 0.15 to 15%" (Frontiers in Medicine review, read 27 September 2026)
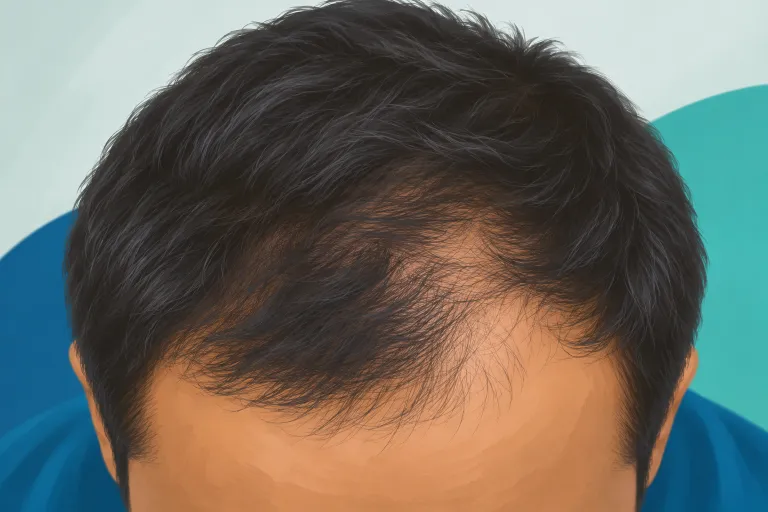
Who's at risk:
- People with miniaturized (thinning) hair
- Women (the review calls female sex a major risk factor)
Prevention:
- Ask your surgeon whether to continue any hair-loss medication you already take.
- Minimize trauma during surgery
Permanent shock loss: "Although typically temporary, a permanent reduction in native hair density may occur, particularly in follicles nearing the end of their growth cycle or already miniaturized" (Frontiers in Medicine review, read 27 September 2026)
Less Common but Manageable Risks
Infection
What happens:
- Bacterial infection in recipient or donor area
- "Postoperative infection after FUE is rare, with most studies reporting an incidence below 1%, although published rates vary across series." The review's table gives the timing as "First 1-4 weeks" (Frontiers in Medicine review, read 27 September 2026)
Symptoms:
- Increasing redness
- Warmth
- Pus/yellow discharge
- Fever (the NHS usually considers 38°C / 100.4°F or above a high temperature; read 8 November 2026)
- Worsening pain
Prevention:
- Antibiotics: "Although many surgeons routinely prescribe oral antibiotics, current evidence does not support their systematic use in hair transplantation, and prophylaxis should, in most cases, be reserved for patients at increased risk of surgical-site infection" (Frontiers in Medicine review, read 27 September 2026)
- Proper wound care
- Keep scalp clean
Treatment:
- Superficial infections usually respond to topical antibiotics. More extensive infections need systemic broad-spectrum antibiotics, per the Frontiers in Medicine review (read 8 November 2026).
Impact on grafts:
- Localized infection: May lose grafts in affected area
- Treated quickly: Usually minimal loss
Folliculitis
What happens:
- Inflamed hair follicles
- Small pimple-like bumps around grafts
- Folliculitis can show up in the donor area, the recipient area or both. "In a large multicenter retrospective study, Zhou et al. reported an incidence of 12.1%." "The onset typically occurs within the first 1-4 weeks after surgery" (Frontiers in Medicine review, read 27 September 2026)
Cause:
- Ingrown hairs
- Bacterial colonization
- Normal part of hair emerging
Treatment:
- Warm compresses
- Antibiotic ointment
- Oral antibiotics if severe
- Usually self-resolving
Usually not serious: "most cases resolve without sequelae; however, extensive or recurrent folliculitis may delay hair regrowth and negatively affect graft survival" (Frontiers in Medicine review, read 27 September 2026)
Cyst Formation
What happens:
- The review's table describes "Small, firm nodules at punch sites or in the recipient area; may become inflamed or infected" and gives the timing as "Weeks to months post-op" (Frontiers in Medicine review, read 27 September 2026)
- The review calls inclusion cysts "uncommon complications following FUE" and says cysts "may also develop in the recipient area, where they are more common, typically arising when a graft is inadvertently buried or inserted over a previously placed follicular unit" (Frontiers in Medicine review, read 27 September 2026)
Cause:
- Grafts placed too deep
- Debris trapped beneath skin
Treatment:
- Observation if there are no symptoms; steroid injection into the cyst; incision and drainage with antibiotics if inflamed; surgical removal if it persists (Frontiers in Medicine review, read 8 November 2026).
Prevention:
- Proper implantation depth
- Meticulous technique
Poor Graft Survival in Specific Areas
What happens:
- Most grafts grow, but certain patches don't
- The review's table gives poor growth's frequency as "Variable" and its timing as "6-12 months post-op" (Frontiers in Medicine review, read 27 September 2026)
Causes:
- Poor blood supply in those areas
- Graft damage during extraction/implantation
- Patient-specific healing factors
Treatment:
- Touch-up procedure (mini-transplant to fill gaps)
- Ask whether the clinic covers a touch-up. Hairsmith in Bangkok says: "After one year, if there are areas where the hair hasn't grown well or hasn't grown at all, we will do a free touch-up without any extra charges" (Hairsmith cost page, read 27 September 2026)
- Ask your surgeon when to assess growth (a 2026 review lists poor growth at 6-12 months after surgery)
Prolonged Numbness
What happens:
- Numbness in donor or recipient area. "Symptoms are typically transient, but persistent cases lasting several months have been reported, with complete resolution usually occurring within 4-8 months." "In a large FUE series, Aksoz et al. reported long-term numbness or paresthesia in approximately 2% of patients, mainly in the temporal or occipital areas" (Frontiers in Medicine review, read 27 September 2026)
- Rarely permanent
Cause:
- Temporary nerve trauma during surgery
- Nerves regenerate over time
FUE: The review links numbness to small nerve fibers cut during the many punch excisions
Concerning: Numbness with weakness (extremely rare, indicates nerve damage)
Rare but Serious Risks
Skin Necrosis (Tissue Death)
What happens:
- Skin turns dark, dies due to lost blood supply
- Caused by overly aggressive graft packing
- The review calls recipient-site necrosis "a rare but potentially severe complication" and says "Its true incidence remains unknown, as only isolated case reports and small series have been published to date" (Frontiers in Medicine review, read 27 September 2026)
Risk factors:
- Smoking (reduces blood flow)
- Diabetes
- Previous scalp surgery/scarring
- Too many grafts packed too close
Prevention:
- Conservative density targets
- Quit smoking 4-6 weeks before surgery (American College of Surgeons, read 8 November 2026)
- Experienced surgeon (knows safe limits)
Treatment:
- Immediate medical attention
- Wound care
Impact: Small areas of necrosis can heal; large areas may need revision
Severe Infection
What happens:
- "Severe infections, occasionally leading to localized tissue necrosis, are uncommon but may jeopardize graft survival and aesthetic outcomes" (Frontiers in Medicine review, read 27 September 2026)
Symptoms:
- Painful swelling
- Fever
Treatment:
- More extensive infections need systemic broad-spectrum antibiotics, per the Frontiers in Medicine review (read 8 November 2026).
Prevention:
- Proper sterile technique
- Clean aftercare
Permanent Shock Loss
What happens:
- Native hair sheds and doesn't grow back
- Leaves thin, patchy appearance
Causes:
- Overly aggressive graft placement (damages native follicles)
- Poor surgical technique
- Pre-existing miniaturization (hair was dying anyway)
Risk factors:
- Advanced hair loss (existing hair already weak)
- High density packing
- Inexperienced surgeon
Treatment:
- Touch-up transplant
- Scalp micropigmentation
- Acceptance
Prevention:
- Conservative approach in areas with miniaturized hair
- Ask your surgeon whether to continue any hair-loss medication you already take.
Keloid or Hypertrophic Scarring
What happens:
- Scar overgrows, becomes raised, thick, and dark
- More common with FUT linear scar
- The review says "Abnormal scarring in the donor area after FUE is rare, especially when compared to the linear scarring associated with FUT." "Although keloidal scarring is exceedingly uncommon and typically limited to case reports, diffuse fibrosis or thickening may occur in some patients, particularly when large punches are used, extraction density is excessive, or spacing between punches is inadequate" (Frontiers in Medicine review, read 27 September 2026)
Risk factors:
- Personal or family history of abnormal scarring (Frontiers in Medicine review, read 8 November 2026)
Prevention:
- Tell surgeon if you have keloid history
- Consider FUE instead of FUT
- May not be a candidate if severe tendency
Treatment:
- Steroid injections
- Silicone sheets
- Laser therapy
Nerve Damage
What happens:
- Permanent numbness or altered sensation
- Rare; one large FUE series in the review reported long-term numbness or tingling in about 2% of patients
Symptoms:
- Numbness that lasts longer than the 4-8 months a 2026 review calls usual
- Burning or tingling that worsens
- Weakness (extremely rare)
Prevention:
- Experienced surgeon
- Proper depth control
Treatment:
- "In cases of persistent sensory symptoms, treatment may include regional infiltrations of local anesthetics and corticosteroids, oral gabapentin or pregabalin, or botulinum-toxin injections" (Frontiers in Medicine review, read 27 September 2026)
Medical Tourism-Specific Risks
Complications from traveling for surgery:
- Limited follow-up access
- Infection develops after you leave country
- Difficult to get timely care
Mitigation:
- Choose facilities accredited by Joint Commission International (JCI)
- Verify surgeon credentials
- Ask your surgeon how many days to stay for follow-up and flight clearance
- Have local follow-up arranged before traveling
Warning Signs: When to Contact Your Surgeon
Immediate (within 24 hours):
- Heavy bleeding that won't stop
- Severe pain not controlled by medication
- Signs of allergic reaction (difficulty breathing, widespread rash)
Within 1-3 days:
- Redness or warmth that keeps increasing, or swelling that keeps getting worse
- Pus or foul-smelling discharge
- Fever (the NHS usually considers 38°C / 100.4°F or above a high temperature; read 8 November 2026)
- Black or dark purple skin (necrosis)
Within a week:
- Scabs not forming
- Excessive crusting/oozing
- Severe itching with redness/swelling
Month 3-6:
- No growth when your surgeon expects it (ask at your follow-up visit)
- Severe patchy growth
- Persistent cysts
Risk Minimization Strategy
Pre-Op:
- Choose a surgeon certified by the American Board of Hair Restoration Surgery (ABHRS) or a member of the International Society of Hair Restoration Surgery (ISHRS)
- Disclose all medical conditions
- Quit smoking 4-6 weeks before surgery (American College of Surgeons, read 8 November 2026)
- Stop blood thinners as directed
- Ask about surgeon's complication rate
During Procedure:
- Verify sterile technique used
- Ask about preservation solutions
- Confirm surgeon performing key steps
Post-Op:
- Take all prescribed medications
- Follow washing instructions exactly
- Sleep elevated
- After surgery, the American College of Surgeons advises staying smoke-free for 4 weeks (read 8 November 2026). Ask your clinic how long to avoid alcohol.
- Attend all follow-ups
Frequently Asked Questions
What are the most common risks after a hair transplant?
A 2026 review of FUE complications says most complications "are mild and self-limited, such as postoperative edema, pruritus, transient pain, or temporary effluvium": swelling, itching, pain and temporary shedding. "In FUE cohorts, frontal edema has been observed in nearly half of patients, making it the most common early postoperative finding." Swelling peaks "around 2-3 days after surgery" and resolves "within 5-7 days." Crusts are "a normal part of postoperative healing after FUE" and resolve "by 7-10 days with appropriate care." Shock loss of your own nearby hair has a reported incidence that "varies widely, ranging from 0.15 to 15%" (Frontiers in Medicine review, read 27 September 2026).
What is shock loss after a hair transplant?
A 2026 review says shock loss "denotes the transient shedding of native hairs surrounding the implanted area." It "typically occurs within 2-8 weeks after surgery, with regrowth usually beginning around 3 months postoperatively. Reported incidence varies widely, ranging from 0.15 to 15%." "Female sex has been identified as a major risk factor." "Although typically temporary, a permanent reduction in native hair density may occur, particularly in follicles nearing the end of their growth cycle or already miniaturized." "Topical or oral minoxidil may help accelerate regrowth" (Frontiers in Medicine review, read 27 September 2026). This is different from the normal shedding of transplanted hairs: "between two and eight weeks after the surgery, the transplanted hair will fall out. This is normal." (American Academy of Dermatology, read 27 September 2026)
What are the signs of infection after a hair transplant?
A 2026 review lists "pustules or honey-colored crusts, increasing pain, swelling, erythema, purulent drainage, and tenderness or enlargement of regional lymph nodes." That means pus spots or yellow crusts, pain that gets worse, swelling, redness, pus, and tender or swollen glands. It says "Postoperative infection after FUE is rare, with most studies reporting an incidence below 1%, although published rates vary across series." "Superficial infections usually respond to topical antibiotics such as mupirocin or clindamycin," while more extensive infections "require systemic broad-spectrum antibiotics" (Frontiers in Medicine review, read 27 September 2026). Contact your surgeon immediately if you notice these signs.
What are the rare but serious risks of hair transplants?
A 2026 review of FUE complications names several. Recipient-site necrosis, where tissue at the implant site dies, is "a rare but potentially severe complication," and "Its true incidence remains unknown, as only isolated case reports and small series have been published to date." "Severe infections, occasionally leading to localized tissue necrosis, are uncommon but may jeopardize graft survival and aesthetic outcomes." "Abnormal scarring in the donor area after FUE is rare, especially when compared to the linear scarring associated with FUT." "Although keloidal scarring is exceedingly uncommon and typically limited to case reports, diffuse fibrosis or thickening may occur in some patients, particularly when large punches are used, extraction density is excessive, or spacing between punches is inadequate." Shock loss is "typically temporary," but "a permanent reduction in native hair density may occur" (Frontiers in Medicine review, read 27 September 2026).
Conclusion
Most hair transplant risks are minor and temporary. Serious complications are rare and usually preventable with proper surgeon selection and aftercare. The single most important risk reduction: choose a qualified, experienced surgeon, not the cheapest option.
If something feels wrong during recovery, contact your surgeon immediately. Early intervention prevents most serious complications.
Next steps:
- Learn proper care: Hair Transplant Aftercare Guide
- Return to complete guide: Hair Transplant Guide
Read next
- Infection after a hair transplantPublished infection rates with their studies, how to tell infection from normal healing and folliculitis, and what to do once home.
- Hair transplant scarsWhat FUE and FUT leave, how short you can cut your hair, how scars are repaired and what Thai clinics and patients say.
- Failed hair transplantWhen to judge growth, how repairs work, donor limits and what Thai clinics publish about costs and touch-ups.
- Second hair transplantReasons to return, waiting times, donor limits, repair plans and costs, with accounts from patients who went back.